Showing posts with label psychiatry. Show all posts

Saturday, December 30, 2017

OB/GYN Ethics 301

In OB/GYN Ethics 101 I went over topics for medical students, residents rotating through OB/GYN settings, and OB/GYN interns. In OB/GYN Ethics 201 I reviewed topics for OB/GYN residents in generalist settings. Now I need to review a few subspecialty concerns with a fine-toothed comb, especially those not focused on pregnancy and maternal/fetal vital conflicts.

Please remember that I'm not a moral theologian. I'm one resident talking to another, and I am happy to engage in discussion and to retract whatever is in conflict with Church teaching.

REI

Img credit: RWJMS IVF Program, Wikimedia commons.
As in OB/GYN 101, observation of almost everything is okay. Observing gives you a better ability to talk to non-healthcare practitioners (e.g. patients, parishioners, priests, even ethicists) about things they may never see.

You can participate in and perform follicle scans, simple procedures such as transvaginal cyst drainage, medical management with provera (or other progestins), letrozole (or other aromatase inhibitors) clomid (clomiphene), follistim (urofollitropin), trigger shots (b-hCG), GnRH pumps, and anything else that won't have post-fertilization side effects.

You can participate in prenatal genetic diagnosis (or screening) with great caution. PGD is a biopsy of a large percentage of a human embryo's body; it's a significant procedure for that little person, but in itself it's a biopsy, not an act of killing or mutilation. If you know or suspect that the embryo being tested may be rejected (destroyed or cryopreserved), this may be proximate cooperation in evil and you may incur some of the guilt in that act. It's rare that the embryologist would let you do this, anyway.

You can observe but not participate in semen washing, egg harvests, and intrauterine insemination (IUI). These replace or interrupt intermediate steps in sex (semen washing replaces filtering and capacitation of sperm; egg harvest interrupts local motion of eggs; and IUIs replace local motion of sperm after ejaculation. (To clarify for those who have done bench research: semen washing of animal samples or of human samples intended for research does not carry the same gravity, even if the human samples were obtained through masturbation. The participation in masturbation is remote, mediate, material cooperation in the evil and does not confer guilt in the act.)

Family balancing by selecting embryos after prenatal genetic diagnosis is immoral; family balancing that includes embryo destruction is gravely immoral. Selective reduction is gravely immoral. Avoid witnessing destruction of embryos or selective reduction. Counsel against selective reduction.

The standard of care is now clomid/IUI for unexplained infertility, followed by homologous or heterologous IVF with embryo transfer (ET) if that doesn't work. But you'll find a lot of acronyms in Catholic bioethical literature. These are mostly from the early days of IVF when people were attempting to find techniques that boosted success rates. Eventually, REIs and ASRM realized that IVF/ET was easier and nothing else made a difference, except for ICSI (see below). Bearing that in mind, here is a quick list of acronyms, defnitions, and comments that you might encounter from bioethicists:
  • GIFT/TOTS: gamete intra-fallopian tube transfer, not permissible because it replaces the marital act, if sex is every involved (e.g. by collecting sperm in a perforated condom) it is only accidental
  • ZIFT: zygote intra-fallopian tube transfer, ethically analogous to ET, which transfers an embryo into the uterus (see below)
  • LTOT: low tubal ovum transfer, moving an egg from the ovary to the isthmus of the fallopian tube or even to the uterus, without removing it from the body is LICIT when there is intention of fertilizing it with an act of intercourse and not IUI.
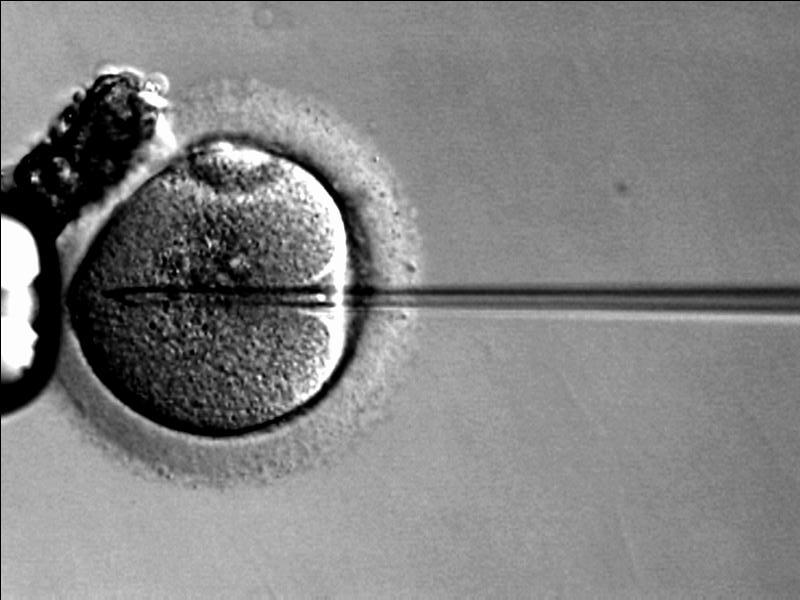
Img credit: RWJMS IVF Program, Wikimedia commons.
Intracellular sperm injection (ICSI) injects a sperm directly into an oocyte (see left). It's used for very abnormal or poorly motile sperm and low sperm count. It replaces part of the sexual act and is not licit; do not participate, although you may observe.

Embryo transfer is a slightly hot topic within bioethics. However, I don't see it as that contentious. Fertilization has already occurred, and the sex act has been totally replaced. The local motion of the embryo into the uterus is actually a step in gestation. It seems that ET, therefore, is not illicit and you should actually rejoice that an embryo is being given its rightful place instead of being condemned to that "absurd fate" of cryopreservation.

INVOcell is a new technology being marketed as "mini-IVF," and it basically replaces the embryology lab with a small plastic capsule carried inside the patient's vagina during a several-day incubation period. This conserves funds used to pay an embryologist, maintain sophisticated lab incubators, and maintain multiple federal standards. INVOcell still involves removal of the egg from the patient or use of a frozen egg, masturbation or sperm donation, fertilization outside the body, and ET. It can still involve PGD and embryo destruction or cryopreservation. Treat INVOcell as you would IVF.

Third party reproduction is use of a gestational carrier or use of donated gametes. As a trainee, there is little to nothing you can do about it, as most couples will come to their REI already with a gestational carrier in mind or will elect to use donated gametes without your counseling. If offered the opportunity to counsel on third party reproduction (especially gestational carriers), offer the patient the complex legal truths surrounding these entities, and recommend they speak to a lawyer, to trusted friends and spiritual leaders, and to seriously consider the possibility of adoption.

Transgender medicine is a misguided effort to alleviate real suffering that individuals feel due to a mismatch between their phenotypic sex and their psychological perception of their gender. Hormonal treatment in these cases, like in cases of fertile women seeking contraception, is manipulation of a healthy organ and not medicine. Surgical transition is mutilation of healthy organs. Do not participate.

Sexual Health

There is a lot of material in treatment of orgasmic disorders that amounts to pornography and masturbation. You may teach a woman the location of her own organs with diagrams and even with a mirror, but be very careful to maintain clinical professionalism and (obviously) always have a chaperone in the room. You may explain the function of these organs and how women experience orgasm (including how they experience it differently). With the magnificent teachings of the theology of the body, reassure women that sex is good, that it is meant to be enjoyed.

You may recommend a patient to psychological or psychiatric services for comorbid disorders. Be careful when recommending her to mental health services simply for her sexual dysfunction, as they may recommend illicit methods to become more comfortable with sexuality. Do not refer her to explicit websites or video series. Do not recommend self-stimulation. Do not recommend experimentation with more than a spouse.

Psychiatry

A relatively prominent problem that has come up since I've started this blog is quality of psychiatry services. Some mental health professionals, especially those who adhere to the whims of the APA, not only have incorrect ideas of sexuality but also have incorrect ideas spirituality and medications. Others are incompetent.

I've seen OB/GYN residents and fellows of all stripes struggle with conflicts with consultants. Bottom line is: if you don't think the provider will offer benefit to your patient, don't consult them. Consult someone else. If there is no one else, use experts available in other venues (online, prior institutions) to answer your clinical question.

Vulvar care

As with sexual health, anything amounting to masturbation should be avoided. In general, the other meds, lubricants, behavioral modifications, and hygiene counseling in vulvar care is licit.

End-of-life (GYN oncology)

Futility of surgery: many, many times residents in my program have operated while not being excited about it, although we're young and maybe don't understand everything. If your conscience moves you to protest a surgery based on a patient's medical fragility, say so and consider escalating it to the ethics committee if you have an appropriate way to do so.

Some oncologists do not give percentages for success for treatment unless a patient asks. Others always deliver expectations. If a patient asks for a percentage of success, always give an evidence-based, up to date number or offer to ask someone for the answer and do not rest until the patient gets an answer or says she doesn't want one after all. If you believe someone is being led to chemo or to hospice out of a wrong idea of percentages of success or failure, ask the attending and ask the patient what their view of the situation is, before wading in.

Ethics committees are great except when they're ineffective or pancretist. When faced with an ethics committee that cannot find the moral truth, many trainees are powerless. It is licit to withdraw your opposition in the face of impossible odds, but it is best to make it clear that you still maintain your position and beliefs.

Hospice is great except when its not. Sadly, since I've started this blog I've realized that not all hospice programs are focused on the patient's autonomy. If hospice personnel at the program that will be covered by the patient's insurance demand code statuses that the patient does not want, or demand POLST or other documents the patient does not want, offer to provide similar services (e.g. narcotic and benzo scripts, DME scripts, megace/nutritional scripts, anticholinergics) through the resident clinic or another venue. Never participate in physician-assisted suicide. Counsel actively against it.

Monday, August 15, 2016

Cognitive Disorders

Medical training and life in general is overflowing with cognitive mistakes. I've been meaning to blog about them since fourth year of medical school. Here are ten common cognitive mistakes; look how close to the truth each one is. (This is reprinted from some handout I got some time in med school. If I'm plagiarizing, let me know and I'll take it down.)
  1. All-or-nothing thinking: you see things in black-and white categories. If your performance falls short of perfect, you see yourself as a total failure.
  2. Overgeneralization: you see a single negative event as a never-ending pattern of defeat.
  3. Mental filter: you pick out a single negative detail and dwell on it exclusively so that your vision of all reality becomes darkened, like the drop of ink that discolors the entire beaker of water.
  4. Disqualifying the positive: you reject positive experiences by insisting that they "don't count" for some reason. In this way you can maintain a negative belief that is contradicted by your everyday experiences.
  5. Jumping to conclusions: you make a negative interpretation even though there are no definite facts that convincingly support your conclusion.
    1. Mind reading: you arbitrarily conclude that someone is reacting negatively to you, and you don't bother to check this out.
    2. The fortuneteller error: you can anticipate that things will turn out badly, and you feel convinced that your prediction is an already-established fact.
  6. Magnification (catastrophizing) or minimization (also called "the binocular trick"): you exaggerate the importance of things (such as your goof-up or someone else's achievement), or you inappropriately shrink things until they appear tiny (your own desirable qualities or another person's imperfections).
  7. Emotional reasoning: you assume that your negative emotions necessarily reflect the way things really are.
  8. Should statements: you try to motivate yourself with "should" and "shouldn't," as if you had to be whipped and punished before you could be expected to do anything. "Musts" and "oughts" are also offenders. the emotional consequences are guilt. When you direct "should" statements toward others, you feel anger, frustration, and resentment.
  9. Labeling and mislabeling: this is an extreme form of overgeneralization. Instead of describing your error, you attach a negative label to yourself. "I'm a loser." When someone else's behavior rubs you the wrong way, you attach a negative label to him. "He's a louse." Mislabeling involves describing an event with language that is highly colored and emotional labeled.
  10. Personalization: you see yourself as the cause of some negative external event, for which in fact you were not primarily responsible.

Sunday, May 3, 2015

Stacy's Story

This post conforms to the blog rules.A patient I met and, in the wash of clerkships, left behind, left an incredible impression on me even though I barely knew her. Almost every detail about this person is altered to protect her.

"Stacy" was a middle-aged woman who became pregnant under extremely bad circumstances. Her family started to notice that she was acting strange. To their alarm, she began to tell them she saw and heard things they could not see or hear: she was hallucinating. The duress of her pregnancy had affected her so severely that she had become disconnected with reality. She went to the emergency room after suffering a psychogenic seizure, and I rounded on her her shortly thereafter.

As I flipped through her chart before going to see her, I asked the nurse what was going on.

"It's crazy," the nurse said, speaking of the situation. She gave me more and more details as I went through the records, underlining hCG values and the ER course. "And her family doesn't want to keep it," the nurse finished.

I froze. Doesn't want to keep it. They wanted an abortion.

"What does she want?" I asked.

The nurse shrugged. "She can't say, most of the time. She has these good times when she makes sense, but sometimes she babbles and acts bizarre. Sometimes she doesn't know she's pregnant when you ask her."

I continued reviewing records mechanically, and went to see the patient, wondering what I could do. The first time I spoke with Stacy was during one of her lucid times. After introducing myself and seating us in a private and comfortable place, I told her I wanted to talk with her briefly and then gently asked her, "What brought you here?"

She gazed at me innocently, almost emptily, with warm brown eyes. "I'm pregnant," she said simply.

"That's right," I said.

"I'm eight weeks," she added.

"Exactly," I said with a smile. "Do you know what that means?"

She shook her head.

"It means your baby's heart is beating," I said, "and he has all his fingers and toes."

"Oh," she said, her voice inflecting for the first time, a little flicker of a healthy mind. "Maybe I'll keep it."

Those were her exact words, and I cannot forget them. The interview went on, and I wrote my progress note and left. At rounds a few minutes later, the story became even more nightmarish as I discovered that my attending and my fellow students were all hoping that she could get an abortion. Perversely, we carefully looked up what psychiatric drugs she should most safely take in pregnancy and consulted a psychiatrist with experience in that. Even as we hoped that Stacy's embryo would be eradicated, we protected that embryo from possible adverse effects of the medicines we prescribed.


The week churned on and I moved away from Stacy's floor while other students worked on her care. I heard new of her remotely when students would talk about her, and the reports were not good: she had fewer lucid times and finally none at all despite changing her medicines. Meanwhile, her family was trying to arrange for an abortion. I stormed heaven and asked friends and family to do the same.

Stacy's case became very complex and the hospital system ethics committee met over a weekend, weeks after her admission, to decide whether she could have an abortion. Her case was described in detail at our rotation's grand rounds, where another student presented and the general feeling among my peers and professors was annoyance that the "stupid" hospital was keeping this woman from her healthcare. I felt dizzy sitting with them, as if I were in a horror movie or some barbaric country.

After that rotation ended, I texted Stacy's attending and asked about Stacy. It was then that I discovered that the first ethics committee did not approve her abortion, but she ended up having one somewhere else.

I have so many sad thoughts about this case, including things like, should I have insisted on seeing Stacy beyond my time on her ward? It wouldn't have been impossible. Should I have talked with her more about her baby? I didn't want to be coercive but I might have saved a life. Should I have at least documented her desire to keep the pregnancy? I'm sure it might have meant something to the ethics committee if it didn't to her attending and my peers. I was afraid to write it, because I worried that her flip-flopping between options would be seen as a sign of worsening psychosis (which wouldn't be good for the baby's survival or for her), and because I didn't want to be accused of disturbing her "decision."

What a hard case! Please pray for "Stacy" and her family, and her little child. She is apparently back to her normal self and out of her psychosis, but she is not finished dealing with what happened to her this year.


This post was a draft for over a year. I marked it as a "perpetual draft," one of a set of posts that will never be released to protect my career and to protect vulnerable patients. But I decided to release it after I matched, and since it has been such a long time since this occurred.

This post was a draft because I experienced a bit of resistance in my psychiatry clerkship from a pro-choice fourth year (who couldn't believe someone wouldn't do this patient's abortion) and from professors (who called me into an impromptu meeting when I asked too many questions about homosexuality and gender identity disorder). Now, I'm putting it out.

Monday, October 7, 2013

Lacey's Story

This post conforms to the blog rules.While working at the psychiatric hospital in admitting, I was sent to speak with Lacey, a girl who came in with her mother. It was up to me to fill out the interview form, do the mental status exam, and decide whether the girl would be admitted to the mental hospital or not. Of course, I would present the case to my attending, who would check my work and (hopefully) catch my mistake, but I still felt like I was being handed a lot of responsibility.

I went to the waiting room and called the girl's name. A middle-school-aged girl and a young woman, baby on hip, stood and followed me to a room. After introductions, I asked Lacey what brought her in. She did not answer, but only looked out the window, away from me. His mother began to speak, and told me a long and convoluted story about marijuana, bad crowds, running away, and fights.

As the mother spoke, I looked at Lacey, who skillfully avoided eye contact with everyone. I had just finished two weeks on the alcohol and drug dependence ward, and so my soul was full of stories that began like Lacey's and ended with hard street drugs, divorces, dead loved ones, and dead dreams. I looked at her and wondered: will you go down one of those paths, or is this just a slightly-more-serious-case of teenage rebellion? And another possibility: is your mom the crazy one? She's the one doing all the talking.

The baby had fallen asleep on Lacey's mother's chest by the time the story was finished.

"Thank you so much for helping me understand," I told her. "I know it's been a long wait for you, but would you mind stepping out so that I can talk to Lacey?"

She left, and I turned to the silent teenager in front of me. She still gazed out the window. Was that a grave silence or a nonchalant silence or a hurt silence or a panicked silence or...?

"Lacey," I said, "I want to hear your side of the story."

Nothing.

"What your mom told me...does that match what happened?"

Nothing. I tried one or two more times. Still nothing.

"Well," I said, taking a new tack, "pardon me while I fill out some paperwork." And so I sat there, across the table from her, checking boxes on the mental status exam. I wanted to show her I wasn't afraid of silence. Several minutes passed.

"You know," I said at last, trying to speak like one seventh-grader to another (or one medical student to another), "I can't make you stay. Finally, you decide whether we can help you or not. Do you think you need help? Do you want to stay?"

A few more seconds of nothing, then Lacey's eyes moved from the window to his lap. Then she nodded. My heart soared, partially with elation at successfully communicating and partially because I thought she really could use the help.

"Okay," I said softly. I didn't follow Lacey after this, but I won't forget this interview soon. Pray for her if you read this.

Friday, September 20, 2013

Don't Rock the Boat! Homosexuality and Gender Identity, Medically Speaking

This post conforms to the blog rules.Caution while challenging the freedom of gender identity! You get called in with three attendings and they have a very polite discussion to make sure you toe the party line.

After our lecture on psychosexual disorders during the psychiatry clerkship, the faculty physician asked whether there were any questions. She is a prim older woman, an excellent and compassionate clinician that I had the privilege of shadowing for a week.

I piped up, because she had just talked about gender identity disorder. "I know homosexuality isn't in the DSM-IV," I said, "but I'm confused about the stage a gay or lesbian person is in right before they come out, when they're uncomfortable in the societal role they're in. Isn't that GID? What I mean is, why is GID a disorder and not homosexuality?"

Oops. I didn't mean to finish that way. I wasn't trying to evangelize or start anyone's wheels turning. Seriously. I just wanted to know how this was consistent. (It turns out there is an answer and I understand that this is sort of consistent now. More on that below.)

Well, the prim psychiatrist asked my peers whether they could answer, and they could. After I had been given an answer, the professor said we could take a break until the next lecture. I stood to get a glass of water as my peers also stood to stretch or get a snack. But I was stopped before I got my drink by the lecturer, who said, "why don't we go ask Drs. J and K about your question?" I obliged, and followed her to another room, where two other psychiatry faculty were lunching and talking.

The lecturer and I sat down, completing the four points of a square. "I will share with you," she said to her colleagues, "a question [mmatins] brought up about gender identity disorder." They mused. They gave the same answer my peers had.

Somehow I got the impression I was being given a talking-to. I was suddenly acutely conscious of my conservative dress and crucifix. Perhaps it was the arrangement of the room, or the abruptness and apparent formality of the meeting, or the fact that they gave the same answer my peers had, or the fact that I was alone with three faculty members, all of whom (I am reasonably confident) disagree with me about whether homosexuality is a disorder.

Anyway, nothing happened and everything was pleasant. I and the professor giving the next lecture left the room. Just an interesting experience....

So, FYI, GID is something described in younger patients (i.e. children under twelve) who are uncomfortable with their gender and its non-sexual dimensions such as dress, play, and future societal role. Homosexuality is described in patients who are sexually attracted to members of their sex. They can identify as masculine or feminine, a unique combination of both, a fluid (throughout life) combination of both, or neither but the defining characteristic of homosexuality is sexual attraction to members of the same sex. GID patients are uncomfortable in their bodily gender; homosexual patients are sexually attracted to the same sex.

It's not impossible that a person with GID be later attracted sexually to persons of their same original biological sex, nor is it impossible that a homosexual person have some discomfort with all the accoutrements of their biological sex. But these persons may carry two diagnoses. I still do not understand why "trans" adults cannot be diagnosed with GID. My attending raised this question but I didn't press it.

So, the moral of the story: pray for children with GID whose parents may be tempted to permit the children to undergo sex-change surgery. Pray for "trans" adults with undiagnosed (not-medically-real-according-to-DSM5) GID who are doing the same thing. Pray for LGBQ adults, who are attracted to members of the opposite sex. And be careful as we (prayerfully and charitably) rock the boat.


AS ALWAYS THIS BLOG IS NOT TO REPLACE THE CARE AND DIAGNOSIS OF TRAINED PROFESSIONALS.

Saturday, August 17, 2013

A patient teaches me how to trust Jesus

This post conforms to the blog rules.I just finished a week working on the trauma floor of the psychiatric hospital. On this floor, patients who have been abused or undergone some other traumatic experience undergo intensive therapy so that they can return to normal functioning. The hospital I am working at is one of the top in the nation for this, so patients come in from out of state to live on this floor and work through their pasts. If ever I went into psychiatry, it would be for this. It has been the most fascinating, intense, and beautiful week of the rotation so far.

There are several patients on this floor with dissociative identity disorder (DID, which used to be called "multiple personality disorder") because of their trauma. I am following three of them. One of them, an older woman named "Bernice," is unforgettable. She underwent a very difficult childhood and has several "alters," all of whom are children.

Bernice is a petite, white-haired woman who uses a walker for stability. I rounded on her the first two days of my week in trauma and learned about her past, her course of treatment, her marriage, her neighbors, her houseplants, and her alters. She was in the hospital now because she was beginning to dissociate again after being integrated for over ten years. She was not co-conscious with two of the alters who had recently appeared, and they had made frank or angry comments Bernice would never have made to others.

"Bernice, how many alters do you have?"

"I don't know," she said. "Before I came in, my therapist was trying to help me meet them. She suggested that, every night before I go to sleep, I ask them to come around a table, and we'd talk about how the next day would work."

My work with other DID patients reveals they often have an inner landscape, so that they can exile alters to islands, meet with alters, put child alters in safe places, and be co-conscious and supervise alters who come out. They describe their alters as "fronting" when they take executive control of the body; they can be "co-conscious" if one is in control and another is standing just behind or listening and thinking about the goings-on of the alter current in front.

"But," Bernice said, reflecting on the meeting strategy, "I would come to the table, but the children would never come." I found it striking that the personalities are different enough to seem to have their own wills. "So," Bernice went on, "my therapist suggested that I find a safe place for them, so that they wouldn't be afraid to meet with me. She had me read the Narnia books. So now we go to Narnia. Have you read the Narnia books?"

I told her I had. Bernice nodded and went on, "so now I go to Narnia, and I start at the lamppost. And Jesus follows me. He's always behind me. Even when I first started therapy, the very first time someone hypnotized me, Jesus was the first thing I saw. My doctor asked me, 'What do you see?' And I said, 'Jesus!' And when the session was over I saw he [the doctor] had tears in his eyes, and I asked him what was wrong and he said, 'Nothing, I just never heard anything so beautiful.'"

Parenthetically, I don't think Jesus is one of Bernice's alters, nor is she hallucinating. He is just such a strong part of her waking life that when she descends into her soul, she finds Him, real and vibrant, waiting to help her. She described her most recent meeting with her alters.

Src
"So Jesus follows me, and we go to look for Aslan. I think we have to find a different place, though, because Aslan represents Jesus and if I have Jesus...well, you see the point. Anyway, this time we went into Aslan's mane and there was a rocking chair and a baby. I sat in the rocking chair and rocked and nursed the baby, and then the children [her alters] began coming out of the shadows. I saw little Bernice [the first alter who ever appeared] and Lucy [an alter she had named after one of Lewis' characters], and about five or six others far off, beyond where I could see their faces. They looked like a paper doll chain, all holding hands. I didn't see Mattie, the one who was so angry. But Lucy I saw clearly for the first time. She had straight brown hair a little past her shoulders."

"And I think," Bernice mused, "Jesus gave me a gift, with the rocking chair and being able to nurse the baby. Because those children have never had a mother, that's the problem. And so when they saw a mother in me, they weren't afraid to come meet me."

I was struck completely speechless. She said more about Jesus: "He's so gentle," she said. "I'm never afraid. Sometimes he disciplines, but He's never unkind."

Another day I went to see her, I found her just as she was leaving group therapy early (which you're not supposed to do; the trauma program is very disciplined, and she apparently had poor group attendance). I softly called out her name.

"Bernice!"

"I hafta go take a nap--" she began, and then she saw me and her face lit up. "Oh, it's you!" she said girlishly. "Okay, I'll come. I thought you were going to be angry that I was leaving."

"No," I said. "Can I talk to you?"

"Sure," she said brightly. "But I have to get a ser'quel first." Seroquel is a drug that the patients are allowed to take as needed for sleep. She said "seroquel" in such a strange way, though. Bernice was an articulate woman and the way she skipped the second syllable was a little too...childlike.

When Bernice and I went into the little office and I closed the door, I asked, "so, who do I get to talk to today?"

And to my amazement, the person in front of me replied, in a pleased but bashful tone, "My name's Mariana."

Emily McGee
And for the next half hour, I talked with Mariana, a seven-year-old girl. Mariana's voice was a higher pitch, her sentence structure was simpler, and she sat like a little girl in the chair, legs drawn up like a little ballerina (whereas Bernice sat like any other older woman with osteoporosis). And Mariana used "we" instead of "I."

"We were thinking about you last night," she said, for instance. "We were thinking about how you have such pretty skin and thought you'd look good in pink, and now you're wearing pink!" And she beamed. She also related to me how pretty her therapist was and what beautiful skin she had.

"Mariana, is this the first time you've come out?"

"Yes," she replied. "It gets so noisy in that group and big Bernice goes away, so I came out. We don't like that group. We hafta talk about our bodies and," she said, looking down at the body of an older woman, "big Bernice used to be really pretty but thirty years of psych meds....so I don't like that group."

"How many girls are there?" I asked.

"There's seven of us," Mariana answered matter-of-factly. "Lucy and little Bernice and--oh! And the one that gets us into trouble when she comes out OOoh!" Mariana made a very exaggerated face of displeasure.

"Mattie?" I asked.

"Yes!" exclaimed Mariana with some surprise. "Did big Bernice tell you?"

"Yes," I said. I wanted to ask more about Mattie, but we ended up talking about the meeting in Narnia, and I got the story from another perspective. "Big Bernice was telling me she rocked the baby, and then she saw little Bernice and Lucy," I said. "And she saw some children holding hands like paper dolls. Were you one of those?"

Mariana was puzzled. I shouldn't have been surprised--after all, it was Bernice who saw the children in the shadows and was reminded of paper dolls. If Mariana was one of those, she wouldn't have that mental image. "I guess so," Mariana said eventually. "But we came because big Bernice looked so motherly. How were we supposed to come to a table if we didn't even know her?"

I learned a lot about Mariana. She told me a little about everyone's history, and how Bernice had to deal with her alters when they first started coming out. Mariana giggled as she recounted some of the troubles that little Bernice caused when she first came out.

"And she was only two! So of course, she di'n't know how to drive. So when big Bernice went somewhere and then we switched, little Bernice didn't want to drive and so we was stuck. And then once little Bernice finally had to drive once, so she got behind the wheel and drove probably twelve miles and hour all the way home. We were so scared! But then she grew up to five, and now we're all seven."

One of the most interesting comments she made was about the group dynamic. Early in the conversation, she saw the blank Progress Note form by my elbow and asked, "Are you going to ask me questions?"

"No," I said, pushing the form away. "I just want to find out more about you. Mostly I just write how people are doing and if they're having a big problem."

Mariana looked worried. "Do you call switching a big problem?"

I shrugged. "No."

She looked visibly relieved. "Some people do," she said secretively. "But it's not fair for only one to be out all the time. We should all get our chance."

Soon, Mariana began to look tired. "We want to go sleep," she said. "And when we wake up, big Bernice will come back."

"Okay, go get some sleep," I said, and sent her on her way. That was yesterday. Today I went to talk with her again (even though I wasn't supposed to round on her) and expected to see Bernice, herself, again.

But Mariana was still out. She looked very tired, even though it was just after breakfast. "I like your chair," she mused sweetly. "It's got a high back, like a queen's chair."

"A queen of Narnia," I said smilingly.

Her face lit up. "You read those books?" she exclaimed. I nodded, and she almost clapped her hands with glee. Just a few days ago, I had told Bernice (big Bernice) the same thing and got a very different reaction.

We talked briefly. "It's hard to look at all those people out there," she said, speaking of the other patients on the trauma unit. "We look at them and see that three-fourths of them will never be well. They will get better, but then they will go back to the hospital. Just like us: we thought we were well, but we weren't. Now we're back in the hospital. We will never be well. We won't."

I gazed at the person speaking to me who had the body of an old woman, the mind of a little girl, and a disease so terrible it ripped her identity into pieces. What an incapacitating condition! (She has trouble with adult friendships and jobs because children come out! Once so functional, she's now in a mental hospital, stuck with problems most people never imagine because they're one whole personality.) I wondered whether I should comfort or reassure her. I didn't, and I am so glad I held my tongue, because she said something I will never forget.

Src
"But you know Jesus? He only gives you what's good. One of the letters that Paul wrote, I can't remember what he says but he asked Jesus to take away something, I don't know what, he asked him three times but Jesus didn't take it away. And that's how it is with us. We think we're at our very worst but we're not. That's when we're giving him the greatest glory. We don't think we can do anything but we can and we do."

I was struck speechless again, this time completely overawed.

What trust! I decided that I have no idea what trust in Jesus really is. I recently read Consoling the Heart of Jesus and thought, "aha, now I know how to trust Jesus!" Formation has been focusing heavily on one simple concept: "God loves me immensely." And so I thought, "aha, I live like a beloved daughter of God so vividly now!"

Nope. I have no idea what trust is. I have no idea what living on divine love is.

Bernice and Mariana do. They walk with Jesus in total simplicity, attached to nothing in this world, not even the hope of being integrated or having a life back. With no vengeance, anger, entitlement, or greed, they walk like children, relying on Him for everything and thanking Him even if nothing seems to come.

At that moment, my attending poked his head in the room. "I'm in here talking with Mariana," I explained, so that he wouldn't address her by the wrong name.

(This is old hat to him; he's been in psychiatry so long that he still has a copy of the DSM-II (we're now in the DSM-5) and he's worked psychoanalysis and trauma for so long that he's apparently legendary. "People come from all over the country to be here," he said shuffingly to me one day, "and part of it's to see me.")

So my attending looked at Mariana and said nonchalantly, "so how long are you all planning to stick around?" He was asking about when she wanted to be discharged. I don't remember what Mariana answered; I was still struck dumb by what she had just said. My attending charted "young alter Mariana out" and we left, but I will never forget that conversation.
Therefore, that I might not become too elated, a thorn in the flesh was given to me, an angel of Satan, to beat me, to keep me from being too elated. Three times I begged the Lord about this, that it might leave me, but he said to me, “My grace is sufficient for you, for power is made perfect in weakness.” I will rather boast most gladly of my weaknesses, in order that the power of Christ may dwell with me. Therefore, I am content with weaknesses, insults, hardships, persecutions, and constraints, for the sake of Christ; for when I am weak, then I am strong.

Thursday, August 15, 2013

Discerning Psychiatry

I just finished by NBME (National Board of Medical Examiners' "shelf exam," the final exam we take after each rotation) for Psychiatry. Earlier this week, I had my OSCE (Observed Standardized Clinical Encounter), which consisted of two thirty-minute SP encounters. Psych is over!

In the past six weeks, I have seen 97 different people in a total of 132 visits, 24 of which were "full involvement," including history, physical, differential diagnosis, and treatment. Of note, 40 of my encounters were with males and 92 were with females. This is probably because 1) More women have psych issues and 2) I selectively picked up women's charts when I could. Also of note, there was only a single Asian patient; all the rest were black (30) or white (93). The largest age group represented were the 45-to-60-year-olds, but that's also slightly off probably because I had to guess on some people.

So, what to think of psych? I'm not sure, to be honest. The hours were decent and I enjoyed talking with patients and being part of their care. It was hard to see so much suffering, but that wasn't demoralizing until I got really tired toward the end. I actually felt a little energized by the opportunity to console people in such dark places. (It was unsatisfying not to have continuity of care with those people!)

Toward the end of the rotation, I had a pretty bad week because I got really fed up with the way mental healthcare works, at least in my county. Managed care and third-party payors seem to have really goofed up care. In my grandparents' generation, people were hospitalized for a year, on average. In the hospital I just finished working at, the average stay is 7-10 days; four weeks for people with really good insurance and the older patients on the geriatric unit, who have no other place to go. It's the worst for the poor and the elderly, who should have special privilege.

I was really upset by the amount of control the insurance companies had over the patients' stays. One patient I saw needed to stay but couldn't, and we pretty much had to turn her out, tearful and still needing help. Another patient I saw couldn't get an outside placement at a nursing home unless the doctors made it look like they'd done something to change his status, so his medications were changed (increased) without need.

To be fair to psych, I was cutting back on my eight-hours of sleep, which I've had since before college. And also to be fair to psych, I wasn't getting a lot of exercise. So, the daily schedule during Psych:
5:30am: wake up, eat breakfast so that we keep the fast!
6:10am: leave for Mass
6:30am: Mass, Morning Prayer, and meditation
8:00am to 12:00pm: work at inpatient psychiatric hospital. Midday Prayer if possible! Commute to...
1:00pm-5:00pm: observe at outpatient psychiatry practice, or sometimes lectures, or (four times) a shift in the admitting department until 11:00pm
6:30pm: home, dinner, Evening Prayer. I'd study sometimes in the evenings, or hang out with my family. Formation once a week!
10:00pm: Night prayer and bed.


So, things I liked about psych:
  1. talking with people about serious stuff
  2. some of the faculty
  3. being independent: writing notes, writing prescriptions (even though my signature still doesn't count)
Things I didn't like about psych:
  1. talking with people about serious stuff ALL THE TIME.
  2. the rest of the faculty (was it just my hyperawareness of abnormal psychology or did some of them have mental illnesses?)
  3. the insurance companies' control
  4. the feeling that none of the problems were actually fixed by the doctor: the therapist did most of the real work and the helpful work (chemicals are great but not as good as therapy, it seems), and the past problems were past and it was too late to prevent them.
  5. not being able to answer people's questions about their conditions and medications.
  6. the slightly demeaning way in which all the doctors talked about the patients
So, some of those (e.g. #2 on the pro's and #4 on con's) are just effects of being a medical student on her first rotation. And some of them are purely situational (the faculty ones). And although I enjoyed talking with people, I got a little fatigued by the end of the six weeks because of the nature of the pathology, the payment system, and the mounting feeling like psychiatry isn't the kind of work I want to do. The attitude it engenders towards patients (#6) and the unhelpfulness (#4) is diametrically opposite to my hopes for myself.

We'll see what family medicine has to offer. Here we go!

Saturday, August 10, 2013

There is so much unfinished philosophy of the mind.

I wish the Catholic Church was still shaping the world! The Middle Ages were so awesome. If the Catholic Church still informed the world, we would inquire about the ethics of a thing or theory before or very shortly after it was discovered/described/invented. And true philosophy would follow the natural arts and sciences, with theology (well served) flowering afterwards.

In my imaginary Catholic world, a physician treating mentally ill patients could have a pocket copy of the compendium of teachings describing how God works in, through, and for the mentally ill and disabled.

Sadly, this is not the case. Instead, I wander the halls of the psych hospital with question marks buzzing in my brain, wondering whether my patients can cooperate with grace or can receive sacraments. I will now have fun flouncing around in the fields of philosophy. Sorry to anyone who actually likes to proceed in an orderly fashion.

Psychosis and Choosing the Good
By nature, a human being has a body with many organs, and a soul with several faculties by nature. According to Aristotle (complemented by modern medicine) the faculties of the soul
  1. special senses (e.g. taste, touch, proprioception),
  2. the common sense (no, not "common sense," but the common sense, which compiles sensory information into a whole),
  3. the imagination,
  4. the passive and active intellect, and
  5. the will.
None of these are synonymous with the person. In fact, the error that a person is synonymous with their faculties is rampant right now: we see it borne out in abortion, contraception, and euthanasia. If it can't ______ (see, hear, feel, think, be aware, etc), it's not a human person or, at least, it's not worth defending in the same way that a human who can ______.

Like the unborn and the elderly, the mentally ill have absent or impaired faculties. I suggest the common sense, the imagination, or the intellect is most affected in them. But does this mean they are not persons? No! Does this mean they cannot accept grace? No. (Their wills exist and can act independently of their intellects, perhaps like mine does when I make an act of the will to accept the God is Triune, although my intellect can only shrug and say, "well, St. Thomas said some true stuff about it, but I'm stumped.")

I tend to identify with my intellect. This is not a true or good thing, as seen above. I fall into the same error as our culture does--I need to be more humble, accepting that I am body and soul, matter and spirit. Even so, it is a smaller error to identify with one's intellect than to identify with one's body. The "best" error, the one closest to the truth, would be to identify with one's will. Maybe the attraction to identifying with the intellect (or will) is an old remnant of Eve's mistake, wanting to see herself like God (who is his intellect and will).

Body and Soul: We're Embarassingly One
How bodily we are! Scholastic education is awesome, but it makes me tend to think soul and body are basically separate. That's impossible to think in a psychiatric hospital.

Bodily illnesses have cognitive consequences. Liver failure? The poisons in your blood that your liver can't take care of will make you forgetful and disoriented. Brain injury, even so suble that we can't see it microscopically? Pseudobulbar affect causes people to burst into tears or laughter with the slightest provocation (or none at all). Schizophrenia is associated with decreased cortical mass. More obvious examples are Kluver-Bucy syndrome, Pick's disease, and frontotemporal dementia.

And mental illnesses have material remedies! I saw at least three patients with extreme and overt psychosis become connected with reality in a few days after giving them antipsychotic drugs! Pills can take away delusions and hallucinations. (One woman insisted that I call her First Lady Savior; I just saw her earlier this week and she is completely coherent and herself again. Thanks olanzapine.) The walls between form and matter are becoming preeeeeetty thin here.

Anyway, I just wanted to muse on these things, because I can't really start chatting it up about form and matter with my fellow medical students or attendings. (I never realized how awesome it was at TAC to sit down at a lunch table and talk about first principles.) Maybe this will jog some interesting thoughts in people and we can muse more in the comments?

Tuesday, July 16, 2013

Mental illness: Why?

I have had to talk to God a lot about patients lately. Specifically, the very psychotic and very addicted patients in the pysch hospital I work at right now.

I see men and women who can't recognize reality any more. Illness has thrust a different world on them! They see and hear things that aren't real, they have well-constructed pasts that aren't real, they can't remember where or when or who they are. Depending on how severe their psychosis is, their families grieve as though they have died.

One woman, "Petra," seemed like a shell of a person. She walked the halls, disheveled and clad in pajamas and a blanket. She stared blankly, spoke little, and had no idea where she was or why she was there. She crawled into other people's beds if they left them empty. And her family could not care for her.

Another woman, "Leah," began to curse at me and yell at people who were not there: she looked off into a corner of the room and yelled, then apologized and insisted that nothing was there, and that she was not crazy, could she be discharged please?

There are less severe cases, too. A young man I met was sure that he had no disease, at least nothing that needed medication. I look at his face and know that he'll see the inside of the hospital again if he decides not to take his meds. And another woman  was clearly splitting (as she idealized me and demonized the doctor, then idealized the doctor a little while later) and was disorganized in her speech and thoughts and future plans.


The other day in Adoration I asked Jesus, "why do you allow this? Don't You want our higher faculties to be intact so that we can follow You?"

I'm so in love with my intellect! I practically identify with it. St. Thomas Aquinas stressed the importance of the intellect in the Christian life. In heaven, the intellect enjoys the sight of God as He replaces concept and phantasm in the Beatific Vision: "since the Divine essence is pure act, it will be possible for it to be the form whereby the intellect understands: and this will be the beatific vision" (IIIQ92A1).

And although it is finally the will by which we choose good and avoid evil, the intellect informs the will of what is good and evil.

So why would God allow some souls to have such intellects that can't distinguish reality from internal stimuli?

In Adoration, I pleaded hard for Maggie, Leah, Petra, and the others. I really wanted them to be well, I didn't want them to be unable to see and choose God's mercy before they died (sometimes the lives of psychotic and mentally ill people is tragically short). I asked for it on their behalf.

I was particularly touched by Leah's condition, and I imagined her, lying as she did in her bed, shrouded in sheets to hide from the inescapable voices she heard. I imagined her like that and my kneeling next to her, both of us before the throne of God. And then I realized that I would not be praying so desperately if it were not for her. She was a little guardian angel to me, spurring me on to greater dependence on God. I have heard parents of disabled children occasionally remark that their children help redirect them daily towards God; Leah was doing this for me.

So maybe God allows mental illness for reasons like that. Let's pray for the mentally ill. (As a side note, Leah is much better now; it's amazing what antipsychotic drugs can do. She's no longer hearing voices and she was discharged.)

Tuesday, July 2, 2013

Psychiatry Clerkship Begins Well

My first rotation is Psychiatry. I know nothing about psychiatry and wouldn't have chosen it as my first rotation, but because I switched with a classmate, this is what I ended up with.

Yesterday was my first day of third year and my first day of my first rotation: psychiatry. The hospital where we do most rotations doesn't have an inpatient psychiatry service, so we go to a psychiatric hospital elsewhere in town. I'm still new to the city and I'm not a great navigator to begin with, so I thought I might have trouble finding the place. I mapped it with my iPhone and with Google the night before, and planned to leave twenty minutes early so that I had some time for U-turns.

Well, I followed the directions and ended up in a manufacturing district of a suburb. Driving around, I thought, "maybe they just put the hospital out here to protect the sensitive nature of the problems?" but after finding nothing but an Urgent Care, I decided to whip out the email that the clerkship coordinator had sent and open the Welcome Letter, which had a map at the end of it.

the map was about two inches square, very pixelized on my phone, and had almost zero streets marked. In my haste, I didn't read it properly and saw that one end of the path landed in a different part of town. Quickly I tried to find that area on my iPhone. Without street markings, I headed in the general direction, hoping that my extra twenty minutes would save me. I got stuck in rush hour on a highway I'd never been on before. I called the clerkship director twice, and the clerkship coordinator once, to no avail.

Still wondering what street I would be looking for, I found myself downtown, where one-way streets, bizarre intersections, and other driving disasters about. My iPhone's map was carpeted with streets, and the map on the welcome letter had very few, with no labels. Where was this psychiatric hospital??

I was trying to trust in Jesus and abandon my on-time self-image to Him, but I started crying at this point. I was already late to orientation (and the 8am time was marked in red on the Welcome Letter) for my first rotation during the year when personal characteristics and first impressions matter so much! I pulled into the parking lot of a random high-rise to ask for directions. As I parked I tried to compose myself. Hoping I wouldn't be towed, I headed toward the door and left my white coat in the car.

Another woman got to the door at the same time I did, and I was so desperate that I blurted out, "can you help me?" My eyes were probably red and my voice was soft and shaky.

"Sure!" she said, concerned. "What do you need?"

I don't remember what I said, but it was something like: "I'm lost. I need to get to ____ Psychiatric Hospital," and as I said it a sob broke out. How embarrassing! Even as I was saying it, I was thinking what a great story this would make if everything turned out well.

Well, it turns out she was on her way to a doctors' appointment. We went into the building together and she took me with her to her OB/GYN's office, where she checked in and she let me ask the receptionist for directions. I repeated to the receptionist that I was looking for the psychiatric hospital. Tears were still welling up in my eyes. (I was now forty minutes late for orientation.)

The receptionist's face was instantly concerned and she offered quickly to find out where it was and print off a map for me. Then she said, "I'll call and verify where they are." I thanked her as she dialed. "Hello," she said, when someone picked up. "Hello, this is ___ at ____ Obstetrics and Gynecology. I have a patient of yours here...."

I didn't hear the rest, I was laughing and going hysterical inside! I wanted to cry, but that was just too funny. I eventually got to the hospital (which was a frustrating few minutes away from the manufacturing district that the iPhone had me visit), an hour late for orientation. However, the clerkship director was very forgiving, and now I have a hilarious story.


